How the Anion Gap Evaluates
The anion gap is a calculated value that helps clinicians assess metabolic acidosis and broader acid-base balance at the bedside. It reflects the relationship between measured electrolytes in serum chemistry, especially the major cations and anions that shape acid-base status. In intensive care, the anion gap is not just a number; it is a quick way to identify whether an electrolyte imbalance is being driven by unmeasured acids, loss of bicarbonate, or a more complex metabolic derangement.
The concept is rooted in buffer systems and charge neutrality. Since routine laboratory values do not directly measure every ion present in plasma, the anion gap infers the “missing” anions by comparing the positively charged and negatively charged components that are routinely reported. A increasing gap often signals accumulation of organic acids or toxins, while a normal gap can point toward bicarbonate loss with compensatory chloride retention.
In critical care, this matters because patients with shock, sepsis, organ failure, or toxicity may deteriorate quickly. An elevated gap can be an early clue to anion gap calculation severe illness even before the full clinical picture is obvious. The anion gap calculator supports rapid clinical interpretation by turning routine lab numbers into a targeted differential diagnosis.
A practical understanding of the anion gap can help clinicians move from raw laboratory values to meaningful assessment of acidemia, bicarbonate deficit, and underlying cause. It is a basic diagnostic calculation, but the clinical meaning often depends on the entire context, including the patient’s volume status, renal function, perfusion, and medications.
How to Work with an Anion Gap Calculator
Entering data into an anion gap calculator starts with entering the essential values from the electrolyte panel. The primary inputs are sodium, chloride, and bicarbonate. Some calculators also include potassium, though many bedside methods exclude it because potassium contributes relatively little to the final result.
The workflow is simple:
- Enter the measured sodium value. Enter the measured chloride value. Enter the measured bicarbonate value. If the calculator includes it, enter potassium. Review the calculated anion gap and assess whether anion gap elevation is present.
In practice, the goal is not just to derive a number, but to integrate it into a systematic assessment of the patient’s acid-base disorder. The result should be interpreted together with the arterial blood gas, serum chemistry, and the clinical scenario. A patient with profound lactic acid accumulation, for example, may show a high gap before severe hypotension is fully documented, while a patient receiving large-volume saline may show a normal gap with a falling bicarbonate level.
The bedside value of the calculator is speed. In critical care, decisions often need to be made before all confirmatory data are back. A rapid calculation helps identify whether the patient likely has high anion gap metabolic acidosis or normal anion gap metabolic acidosis, which then directs further workup and treatment priorities.
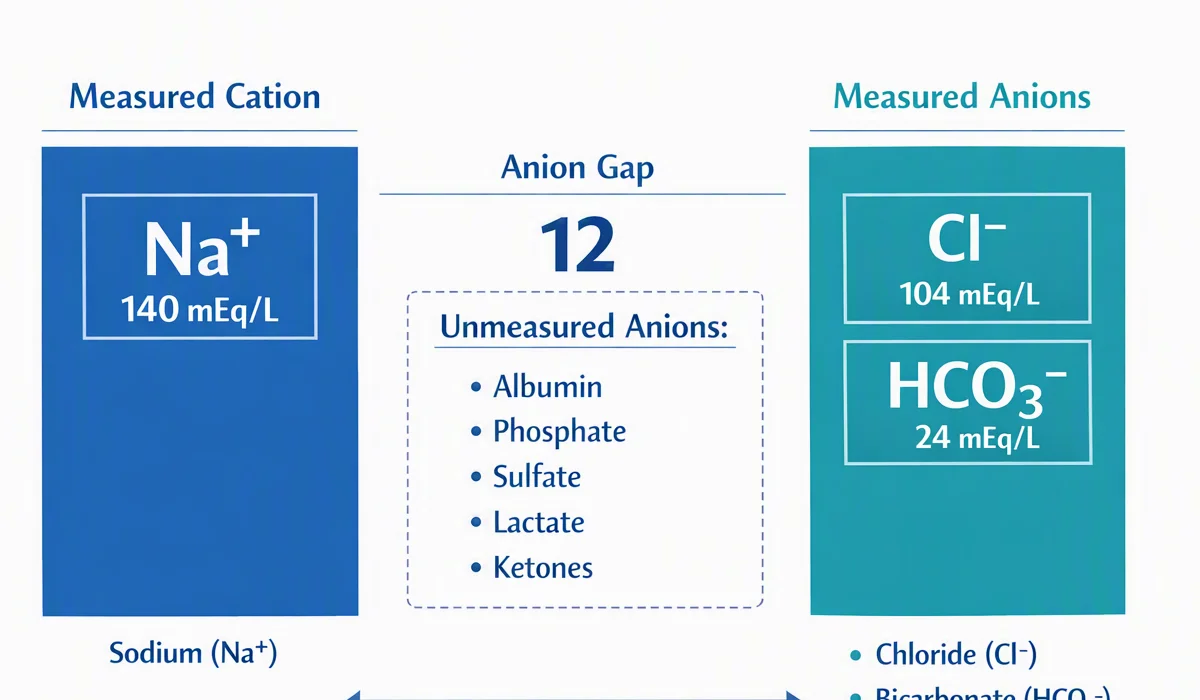
Formula for Anion Gap and Reference Ranges
The classic anion gap formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
If potassium is added, the formula changes to:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
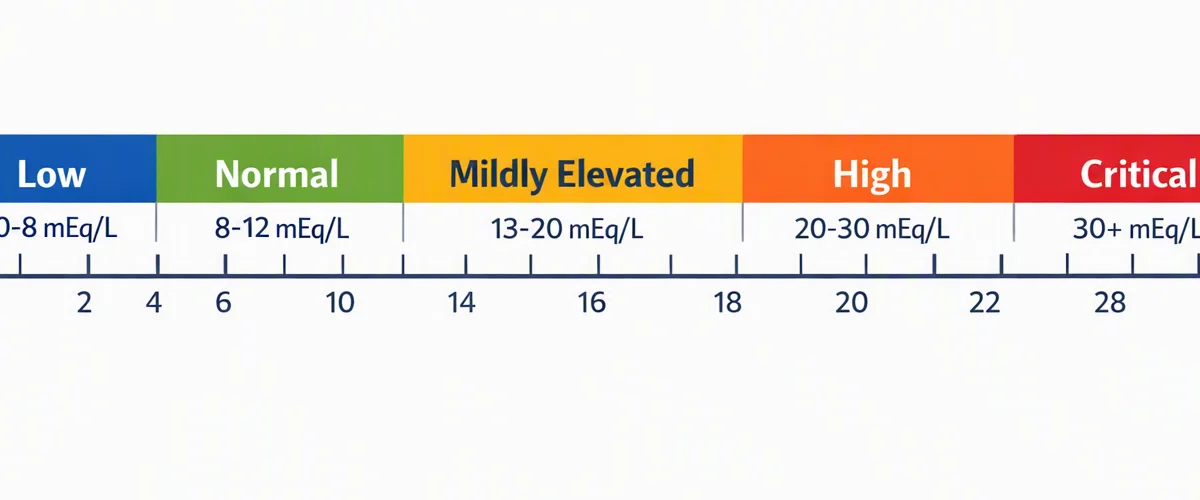
The normal anion gap range varies with the laboratory method and whether potassium is included. Because different analyzers and reference ranges differ, clinicians should use the local lab reference interval rather than relying on a single universal cutoff. Even so, a clearly elevated result should lead clinicians to consider metabolic acidosis and potential unmeasured anions.
One of the most important refinements in ICU practice is albumin correction. Since albumin is a key unmeasured anion, low albumin can mask a clinically important gap. In patients with hypoalbuminemia, the measured anion gap may appear normal even when significant acids are present. A corrected anion gap adjusts for this and improves accuracy in clinical interpretation.
The idea of anion gap correction is especially useful in critically ill patients because critical illness commonly lowers albumin through inflammation, capillary leak, dilution, and reduced synthesis. When albumin falls, the apparent gap falls too, which can obscure a dangerous metabolic state.
For this reason, a clinician evaluating metabolic acidosis should consider both the measured and albumin-corrected anion gap. This is not a minor detail; it can alter the differential diagnosis and influence whether the patient is classified as having high-gap or normal-gap acidosis.
Reading a Increased Anion Gap in Intensive Care
A increased anion gap usually means there are extra unmeasured acids in the blood. In critical care, the key causes include lactic acidosis, ketoacidosis, uremia, and toxic alcohols. These diagnoses carry weight because they frequently reflect severe physiologic stress or poisoning and require prompt action.
Lactic acidosis is common in patients with shock, sepsis, hypoxia, poor perfusion, or mitochondrial dysfunction. A worsening serum lactate in the setting of an elevated anion gap often suggests tissue hypoperfusion or impaired oxygen utilization. In these patients, the gap can serve as a indicator of worsening illness and response to resuscitation.
Ketoacidosis may occur in diabetes, starvation, or alcohol-related states. The organic acids generated during ketone accumulation increase the gap and lower bicarbonate. A bedside anion gap calculator helps identify the acid-base pattern early, especially when glucose is not dramatically elevated or when the presentation is mixed.
Uremia from kidney failure is another frequent cause. As renal clearance declines, retained acids lead to high anion gap metabolic acidosis. In these cases, the anion gap is one clue among several, including rising creatinine, reduced urine output, and worsening overall acid-base status.
Toxic alcohols such as methanol and ethylene glycol can produce a serious gap elevation. These ingestions can be deceptive, and the patient may initially have nonspecific symptoms. A high gap with appropriate clinical features should raise concern for poisoning, especially if the history is incomplete or unavailable. Here, the anion gap is part of a broader toxicity evaluation rather than a standalone answer.
High-gap acidosis is often a race against time. The value itself does not identify the exact cause, but it limits the problem quickly and directs the next test. In ICU settings, that means looking immediately at lactate, ketones, renal function, medication exposure, and osmolar considerations while monitoring the arterial blood gas and hemodynamics.
Reasons of a Normal Anion Gap Acidosis
A normal gap does not necessarily mean the patient is stable. Normal anion gap metabolic acidosis can still represent significant illness, especially when the bicarbonate is low and the patient is acidemic. The classic mechanism is loss of bicarbonate with compensatory retention of chloride, often called hyperchloremic acidosis or hyperchloremic metabolic acidosis.
One common cause is diarrhea, which leads to gastrointestinal bicarbonate loss. Another is renal tubular acidosis, where the kidneys fail to excrete acid or reabsorb bicarbonate properly. Both may produce a low bicarbonate with a normal measured gap, and both require attention to the underlying cause rather than simply correcting the number.
Saline infusion is an particularly important ICU cause. Large volumes of chloride-rich fluids can lower bicarbonate and raise chloride, creating a normal-gap acidosis. This is not just a laboratory curiosity; it can alter acid-base balance during resuscitation and may complicate the interpretation of subsequent labs.
Clinicians should remember that a normal gap can also coexist with other processes. For example, a patient may have renal tubular acidosis plus lactic acidosis, or diarrhea plus ketoacidosis. That is why the anion gap should be interpreted as part of a broader systematic assessment rather than as a standalone discriminator.
In practice, the question is not only whether the gap is normal, but whether the pattern fits the clinical scenario. A low bicarbonate with a normal gap should prompt evaluation for gastrointestinal losses, renal acidification defects, chloride load, and less obvious mixed disorders.
What Makes Albumin Important in ICU Patients
Albumin has a central role in assessing the anion gap because it is a major unmeasured anion. In critical illness, hypoalbuminemia is extremely common due to inflammation, dilution, capillary leak, and reduced hepatic production. When albumin falls, the measured anion gap may miss the true burden of unmeasured acids.
This is why the albumin-corrected anion gap is particularly useful. Without correction, a patient with major metabolic derangement can appear to have a falsely normal gap. That creates a risk of missed diagnosis, delayed treatment, and incomplete clinical interpretation.
The physiologic reason is linked to protein binding. Albumin contributes negatively charged sites that serve to balance cations in plasma. As albumin decreases, those negative charges disappear from the calculation framework, so the observed gap falls even if pathologic acids are accumulating.
For ICU patients, the practical takeaway is clear: if albumin is low, always consider anion gap correction. This is especially important when evaluating suspected metabolic acidosis, unexplained acidemia, or ambiguous laboratory patterns. A corrected value may reclassify the patient from normal-gap to high-gap acidosis and change the differential diagnosis.
Albumin correction does not replace clinical judgment. It increases the precision of the bedside assessment by accounting for the altered baseline chemistry of the critically ill patient. In that sense, it makes the anion gap formula more clinically meaningful when the patient’s protein profile is abnormal.
Frequent Problems and Clinical Pearls
A number of factors can skew an ostensibly simple calculation. The first is lab error. A false sodium, chloride, or bicarbonate result can yield an incorrect gap, so unusual findings should be checked against the clinical picture and, if needed, repeated.
Another common pitfall is the presence of mixed acid-base disorders. A patient may have a high gap acidosis plus a metabolic alkalosis, respiratory disorder, or a simultaneous normal-gap process. In such cases, the anion gap alone may hide the complexity of the acid-base disturbance.
The delta gap is a valuable tool for detecting hidden mixed disorders. By comparing the increase in anion gap with the fall in bicarbonate, clinicians can judge whether there is an additional metabolic process beyond the primary high-gap acidosis. This aids refine bedside reasoning when the numbers do not fit neatly into one category.
Blood gas interpretation is also essential. The anion gap may suggest a metabolic cause, but the arterial blood gas defines pH, respiratory compensation, and overall severity. A patient can have a large gap but near-normal pH if compensation or another disorder is present. Conversely, a modest gap can still be clinically dangerous if compensation is failing.
Further pearls include the following:
- Consistently check albumin when the gap seems unexpectedly normal. Do not assume a high gap is always lactate; evaluate for ketones, renal failure, and toxins. Look for chloride shifts when the bicarbonate is low but the gap remains normal. Use the delta gap when the picture suggests more than one disorder.
These are the details that turn an anion gap calculator from a numeric tool into a genuine aid for critical care decision-making.
Simple Clinical Process for Immediate Use
A hands-on bedside approach can speed up clinical decision-making when a patient shows up with suspected acid-base imbalance. Begin with the electrolyte panel and compute the anion gap without delay. Then check the ABG to determine whether there is acidemia, evaluate respiratory compensation, and decide whether the process is metabolic, respiratory, or mixed.
Next, check serum lactate if the patient is unstable, septic, hypotensive, or otherwise at risk for tissue hypoperfusion. A elevated lactate can explain the gap and support urgent resuscitation. If ketoacidosis is possible, check ketones and glucose. If kidney failure is present, evaluate for uremia. If toxin exposure is possible, suspect toxic alcohols and other causes of toxicity.
Then use albumin correction when indicated. In the ICU, hypoalbuminemia is common enough that a measured gap alone should seldom be the final word. If the corrected value is elevated, reinterpret the problem as high anion gap metabolic acidosis even if the uncorrected number seems borderline.
Finally, bring together everything into the bedside plan. Ask whether the pattern reflects perfusion failure, renal dysfunction, acid generation, fluid-related chloride gain, or a combination of factors. This approach promotes faster recognition of metabolic acidosis and more accurate treatment choices. The calculator is most valuable when it informs a broader systematic assessment rather than an isolated result.
Frequently Asked Questions
What does an anion gap calculator do?
An anion gap calculator is used to quickly assess metabolic acidosis by comparing common serum electrolytes and inferring the presence of unmeasured anions. In critical care, it helps with rapid clinical interpretation, especially when evaluating acid-base disturbances, lactic acidosis, ketoacidosis, renal failure, or toxin exposure.
How do you determine the anion gap in critical care?
Apply the anion gap formula: subtract chloride and bicarbonate from sodium. Potassium is included by some clinicians, but not by many. In critical care, the value should be read alongside the arterial blood gas, serum lactate, and the rest of the electrolyte panel so the calculation supports meaningful bedside judgment.
At what point should the anion gap be corrected for albumin?
Adjust the gap when albumin is low or when hypoalbuminemia is likely, which is common in critical illness. Because albumin contributes to the unmeasured anion pool, low levels can mask a true acid load. Albumin correction and the corrected anion gap improve detection of significant metabolic derangement.
What are the causes of a high anion gap metabolic acidosis?
The main causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, uremia, and toxic alcohols. There are other causes, but these remain the primary ICU considerations. The elevated gap reflects accumulation of unmeasured acids and should trigger a focused differential diagnosis and urgent clinical assessment.
Is it possible for a normal anion gap to appear with serious illness?
Indeed. Normal anion gap metabolic acidosis can still occur in serious illness, especially with hyperchloremic acidosis, renal tubular acidosis, diarrhea, or saline infusion. A normal gap does not exclude clinically important disease, so it must be interpreted in the full context of the patient’s acid-base status, blood gas, and overall condition.