What exactly is an Anion Gap?
The anion gap is a calculated value used to interpret an electrolyte panel and recognize abnormalities in acid-base balance. It contrasts the major measured serum electrolytes to determine whether there are extra unaccounted-for acids or other charged particles in the blood. In practical terms, an anion gap calculator gives a fast snapshot of whether the chemistry pattern suggests a subtle metabolic issue.
Because the bloodstream must remain electrically balanced, the measured cations and anions do not perfectly correspond. The gap is the anion gap. This makes it a useful diagnostic clue in evaluating an acid-base disorder, especially when metabolic acidosis is suspected. Clinicians often use the result as a screening tool before determining whether more testing is needed.
The concept is most relevant when paired with the rest of the serum chemistry picture. Sodium, chloride, and bicarbonate are the main measured values, but the result can also indicate the presence of unmeasured anions such as organic acids or albumin-related charges. That is why the anion gap is not just a number; it is part of a more complete clinical interpretation process.
In What Way the Anion Gap Calculator Functions
An anion gap calculator relies on a basic formula based on sodium, chloride, and bicarbonate. The traditional anion gap formula is:
Anion gap = Sodium - (Chloride + Bicarbonate)
This calculation describes the space between the primary measured positive and negatively charged ions in the blood. Sodium is the highest measured cation in routine lab testing, while chloride and bicarbonate are the main measured anions. The connection among these values can show whether the body has built up acids that are not directly measured on a routine panel.
The calculator does not identify a disease by itself. Instead, it gives interpretation that can narrow the differential diagnosis. For example, a elevated result suggests increased acid burden, while a low result may point toward decreased protein charge, measurement https://anion-gap-calculation.com/causes/high.html issues, or unusual electrolyte patterns. The value of the tool is its clinical utility: it rapidly connects the numbers to likely physiology.
Some versions of the calculation include potassium, but many standard clinical approaches use sodium, chloride, and bicarbonate alone. For most users reviewing an electrolyte panel, the streamlined equation is the most well-known and most convenient to apply.
Calculating Anion Gap From a Basic Metabolic Panel
A basic metabolic panel usually contains the information needed for the determination: serum sodium, serum chloride, and serum bicarbonate. Once those numbers are available, the formula is straightforward and can be done manually or with an online tool.
To calculate the anion gap from a basic metabolic panel, apply these steps:
- Find the serum sodium value. Identify the serum chloride value. Find the serum bicarbonate value. Sum chloride and bicarbonate together. Subtract that sum from sodium.
The result is the anion gap. Since the panel is standardized serum chemistry, this is a quick way to obtain a calculation that helps guide evaluation of a possible metabolic disturbance.
For instance, if sodium is 140, chloride is 104, and bicarbonate is 24, then 104 + 24 = 128, and 140 - 128 = 12. That value may be within the expected reference range depending on the laboratory method used. The important point is not just the number itself, but how it fits with the rest of the lab values and the patient’s condition.
Normal Anion Gap Range and Reference Ranges
The typical range for anion gap is determined by the laboratory and its chosen testing method. Various analyzers and reporting systems can produce marginally different reference interval values. That means the same result may be considered normal in one lab and borderline in another.
One major factor is albumin, a negatively charged plasma protein that affects the apparent gap. Because albumin carries much of the unmeasured negative charge in blood, lower albumin can lower the measured anion gap. This is one reason the result should always be read in the full picture rather than treated as a standalone diagnosis.
Laboratory variation matters as well. The technique used for electrolyte measurement can affect the reported value, so the local reference interval should be used whenever possible. In practice, clinicians focus on whether the number is clearly elevated, reduced, or unexpectedly normal given the acid-base picture.
In some settings, a slightly higher or lower result may still be acceptable if the overall clinical picture does not suggest a significant disorder. That is why the anion gap is best viewed as part of broader clinical interpretation rather than as an isolated cutoff.
Elevated Anion Gap vs Typical Anion Gap Metabolic Acidosis
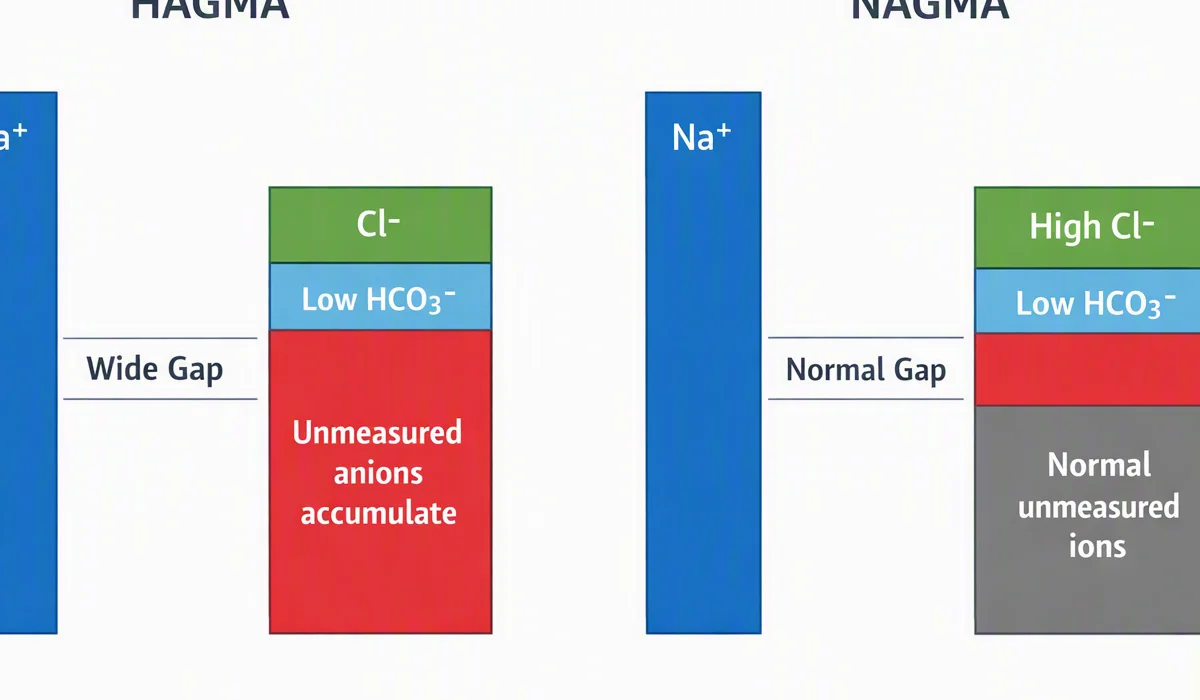
A metabolic acid buildup stands as a leading one of the main reasons to measure an anion gap. A increased anion gap typically indicates that additional acids are circulating in the blood, boosting the number of unmeasured negatively charged particles. A typical anion gap acidosis, by contrast, indicates that bicarbonate has been lost and replaced by chloride, so the overall gap remains about the same.
In a high anion gap state, acid is added to the body faster than it can be removed or buffered. In a normal anion gap pattern, the main problem is often a shift in chloride and bicarbonate rather than an increase of new acids. That distinction helps direct the list of possible causes and guide the next steps in evaluation.
Knowing the relationship between the gap and acid base balance also helps explain why the result matters. The body uses buffer systems to maintain stable pH. When those systems are exceeded, the chemistry panel may show a higher gap or a normal gap pattern that still reflects significant disease.
A decreased anion gap is uncommon but can occur when albumin is reduced, when unmeasured cations are present, or when there is measurement artifact. It should not be ignored if it is unexpected, because it may be a clue to a different issue affecting the serum chemistry pattern.
Typical Causes of an Elevated Anion Gap
An elevated reading often points to the build-up of acidic substances or other charged substances that are not directly captured in the panel. The most common causes include lactic acidosis, ketoacidosis, renal failure, and toxin ingestion.
Lactic acidosis occurs when lactate builds up, often because tissues are not receiving enough oxygen or because metabolism is otherwise stressed. This generates extra acid and raises the anion gap. Ketoacidosis, including diabetic ketoacidosis and other ketosis states, can also raise organic acids in the blood and expand the gap.
Renal failure can result in acid retention because the kidneys are no longer clearing acids effectively. As acid accumulates, the anion gap rises. Toxin ingestion is another important category because certain ingested substances produce acids or interfere with metabolism, causing a significant gap elevation.
Other causes can also be present, but these major categories are central to interpretation. An elevated result is not a final diagnosis; it is a cue to review symptoms, history, and additional labs. That is why the anion gap is best used as a diagnostic clue rather than a standalone answer.
Why Decreased Albumin Affects the Anion Gap
Albumin powerfully influences the anion gap because it provides negative charge to the plasma. As albumin is low, the measured gap can appear lower than expected even if the underlying acid-base status is abnormal. This is why hypoalbuminemia can conceal a clinically important problem.
A anion gap correction compensates for low albumin to more reliably reflect the true acid-base state. The need for correction arises from albumin’s role in protein electrical charge and the spread of charged particles in plasma. Without this adjustment, a patient with significant metabolic disturbance may appear to have a less impressive result than they actually do.
The exact correction method can differ, but the overall idea is the same: lower albumin means the uncorrected number may underestimate the true gap. A corrected value can therefore improve medical interpretation, especially when symptoms or other lab findings suggest acidosis.
Because albumin is so significant, any abnormal result should be reviewed alongside the protein level if available. This is particularly relevant when the anion gap appears normal despite signs of metabolic acidosis.
Step by Step Example Applying an electrolyte panel
Below is an illustrative calculation using standard electrolyte values in an electrolyte panel:
- Serum sodium: 138 Serum chloride: 100 Bicarbonate: 16
Step 1: Sum chloride and bicarbonate. 100 + 16 = 116.
Next: Subtract the total from sodium. 138 - 116 = 22.
The anion gap is 22.
This result is elevated in many reference systems and suggests a likely high anion gap pattern. The next question is not simply whether the number is high, but what the clinical context shows. If the patient has diabetes, poor intake, or vomiting, ketoacidosis may be a concern. If there is shock, infection, or low oxygen delivery, lactic acidosis becomes more likely. If kidney function is poor, renal failure may explain the finding.
Next, examine the same patient with an albumin of 2.5. In this situation, the uncorrected value might miss the degree of abnormality. A adjusted anion gap can offer a more accurate reading and better show the true metabolic disturbance. This is the reason the calculator is most useful when paired with the full lab picture rather than used in isolation.
Limitations of the Anion Gap Calculator
As with any screening tool, an anion gap calculator has limits. One key problem is measurement error. Small differences in how sodium, chloride, and bicarbonate are measured can change the final number, especially when the result is near the boundary of the reference range.
Lab methods too count. Different analysis technologies and electrolyte testing methods can yield diverse results, which is why the laboratory’s reference interval should always be used. A value that looks out of range in one setting may be acceptable in another.
One more limitation is the impact of unmeasured cations. Substances such as lithium or other positively charged ions can alter the calculation and reduce the apparent gap. Moreover, abnormal protein levels, changes in plasma proteins, and unusual clinical situations can create patterns that do not fit a simple formula.
In the end, the calculator cannot replace clinical interpretation. Symptoms, vital signs, blood gas results, kidney function, and glucose or lactate levels may be needed to understand what the result really means. The calculation is helpful, but it is only one piece of the assessment.
When to Seek Urgent Medical Evaluation
Some anion gap abnormalities suggest a potentially dangerous illness that requires prompt attention. If there are signs of severe acidosis, the situation may become urgent quickly. Warning signs can include rapid breathing, confusion, marked weakness, severe nausea, vomiting, abdominal pain, or decreased responsiveness.
Extremely abnormal results or other critical values on the chemistry panel may signal a serious metabolic problem. When the gap is high and the patient is ill, immediate evaluation may be necessary to determine whether there is lactic acidosis, ketoacidosis, toxin exposure, or kidney failure.
Because the anion gap is a diagnostic clue, not a diagnosis, symptoms and the overall picture should guide the response. If there is concern for severe illness, emergency care is appropriate. Delay can be dangerous when the body is struggling to maintain acid-base balance.
Frequently Asked Questions
What is the anion gap on an electrolyte panel?
The anion gap is a calculated value from an electrolyte panel that helps assess acid-base balance. It estimates the difference between measured cations and measured anions, mainly using sodium, chloride, and bicarbonate. It is often used as a screening tool for metabolic problems.
How do you calculate anion gap using sodium, chloride, and bicarbonate?
Apply the formula for anion gap: sodium minus chloride plus bicarbonate. In other words, Anion gap = serum sodium - (serum chloride + serum bicarbonate). This is the common computation used in an anion gap calculator.
What does a high anion gap mean?
A high anion gap usually suggests that unmeasured acids are present, which is a typical pattern in acidic metabolic states. Common causes include lactic acid buildup, ketone buildup, renal insufficiency, and poison exposure. It is a clue that further workup is needed.
How does low albumin change the anion gap?
Serum albumin carries negative charge, so low albumin can lower the measured anion gap. In that case, a albumin-corrected anion gap may better reflect the real acid-base condition. Low albumin can hide an important elevation if the result is not compensated.
Can an anion gap that is normal still be abnormal in acid-base disorders?
Absolutely. A normal gap does not rule out an acid-base disorder. Some forms of metabolic acidosis keep the gap normal because bicarbonate loss is balanced by chloride gain. That is why the result must be interpreted with the rest of the test results and the full clinical picture.